

Most small practices begin an AI conversation by watching a demo or reading a feature comparison. That sequence almost always leads to the same problem: the tool looks useful until someone asks what data it will see, who will review its output, and what happens when the output is wrong. By the time those questions surface, staff time has already been spent and expectations have already been set. The more durable approach is to map the surrounding system first.
Before any AI tool is tested in a behavioral-health practice, three maps need to exist on paper: the data that will move, the people who will touch it, and the decisions that will remain human. Without those maps, even a careful pilot can expand into something the practice cannot later explain or control. This article walks through the practical mapping process we used inside a five-to-fifteen-person clinic.
Start With the Workflow, Not the Product
The first step is to name the specific administrative or operational task under consideration. Vague goals such as “use AI for notes” or “speed up intake” are not maps; they are aspirations. A usable starting point looks more like this: “After a new patient completes the digital intake form, create a short internal checklist for the front desk that flags missing insurance verification and preferred contact method.”
Once the task is named, list every data element the current process already uses. Include both structured fields and free-text notes. Then mark which of those elements would need to leave the practice environment if an external tool were introduced. That single list often reveals more risk than any vendor questionnaire.
In our experience the list almost always includes at least one element that should never leave the building. Identifying it early prevents the common pattern of discovering the problem after the pilot has already begun.

Map the People Who Will Touch the Output
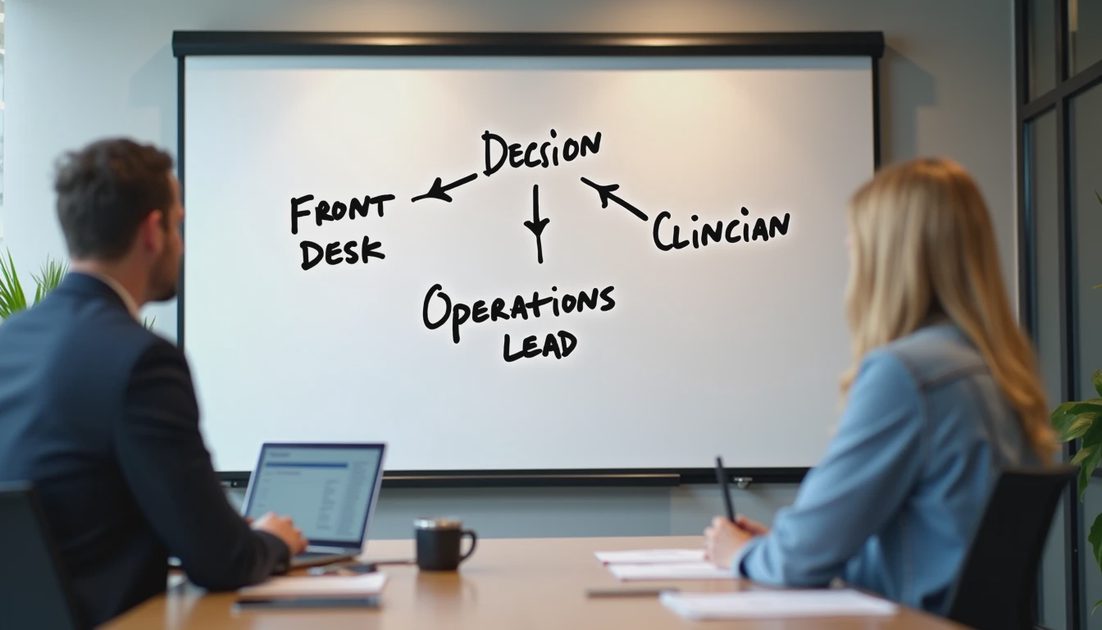
Every AI-generated draft or summary will be seen, edited, or acted on by someone. Name those people by role, not by name. Typical roles in a small practice include:
The staff member who initiates the process
The person who reviews the AI output before it is used
The clinician who may later rely on the resulting documentation
The operations lead who monitors exceptions
For each role, write one sentence that describes the exact decision that person owns. Example: “The operations lead decides whether the AI checklist is complete enough to trigger a patient message.” Ambiguity here is expensive. When ownership is unclear, review becomes a shared hope rather than a scheduled step.
We also map the access permissions that already exist inside the EHR and any related systems. An AI tool that requires broader permissions than current staff accounts will force a change in access policy. That change needs its own decision and its own documentation.
Decisions That Cannot Be Delegated
Certain decisions remain human even when the tool is excellent. These usually include:
Whether a particular patient case should enter the AI workflow at all
Whether the AI output is accurate enough to use
Whether an exception should be escalated or simply logged
Whether the pilot itself should continue or stop
Writing these decisions down before testing begins creates a shared reference when pressure increases later. The tool doesn’t sign the note. You do. Keeping that sentence visible on the map prevents quiet expansion of scope.
Map the Supporting Infrastructure
Before any login is created, answer the following practical questions in writing:
Where will the AI-generated output be stored, and for how long?
Who can delete or correct that output?
What happens to the data if the vendor relationship ends?
How will staff be trained on the new steps, and who will update the training when the workflow changes?
What single form or log will capture exceptions and near-misses?
These questions are not theoretical. They surface the operational cost of the tool long before the monthly invoice arrives. A small practice that cannot answer them is not ready to test, regardless of how attractive the feature list appears.
A Simple Mapping Template That Fits Real Capacity
We use a one-page template that forces the three maps onto a single sheet. The top third lists the data elements and marks which ones may leave the environment. The middle third lists roles and the decision each role owns. The bottom third lists the five infrastructure questions and the current answers. If any section is blank, the pilot does not start.
The template is deliberately short. Long policy documents gather digital dust. A one-page map that is actually filled out and kept in the shared folder is more useful than a thirty-page risk assessment that no one opens after the kickoff meeting.
Completing the map usually takes one focused meeting and a few days of follow-up. That time is not delay; it is the minimum investment required to keep the later work defensible. Slow is not the same as behind. Practices that skip the mapping step often spend far more time later cleaning up an experiment that expanded past its original boundaries.
That’s a judgment call, not a tool question. Mapping the data, the people, and the decisions before any test begins is how a small behavioral-health practice keeps control of its own operating system.